Left untreated, vascular erectile dysfunction is progressive — and it may be signalling a more serious underlying problem. Reasons to seek assessment and treatment:
Arterial ED is often the earliest sign of atherosclerosis — the same disease that causes heart attacks and strokes. ED may precede a cardiac event by 2–5 years in men with cardiovascular risk factors.
Gradual worsening without treatment — as atherosclerosis progresses and cavernous smooth muscle degenerates, options narrow and endovascular treatment becomes less effective
Impact on relationships and psychological wellbeing — untreated ED significantly affects self-esteem, partner relationships, anxiety, and quality of life
Venous leak from Peyronie's disease worsens without treatment — structural tunica albuginea damage progresses and curvature increases
Endovascular treatments (angioplasty, venous embolisation) work better in earlier-stage disease than in severe long-standing cases
If you are exploring vascular ED treatment in Hyderabad, Citi Vascular Centre, KPHB, offers personalised, evidence-based care based on your specific vascular mechanism — all consultations strictly confidential
Clinical History and IIEF Score — severity and pattern of ED documented; onset (gradual vs sudden), morning erections, PDE5 inhibitor response, cardiovascular risk factors
Hormonal Profile — testosterone, LH, prolactin, TSH: to exclude hormonal cause before vascular assessment
Pharmacological Penile Doppler Ultrasound — GOLD STANDARD. After intracavernosal PGE1 injection: PSV (peak systolic velocity), EDV (end-diastolic velocity), RI (resistive index) measured. Classifies arterial vs venous vs mixed ED
CT Pelvic Angiography (CTA) — for arterial ED: maps the internal pudendal artery stenosis to plan angioplasty
Pelvic Venography — for venous leak: maps cavernous vein and pudendal vein drainage before embolisation
Nocturnal Penile Tumescence (NPT) Testing — when psychogenic vs organic distinction is uncertain
|
Doppler Finding |
Diagnosis |
Endovascular Treatment |
|
PSV < 25 cm/s |
Arterial insufficiency — not enough inflow |
Internal pudendal artery angioplasty |
|
EDV > 5 cm/s + RI < 0.75 |
Venous leak — blood escapes too fast |
Pelvic venous embolisation |
|
Both PSV low + EDV elevated |
Mixed — arterial + venous |
Arterial first → reassess venous |
|
Normal PSV + Normal EDV |
Neurogenic / psychogenic |
Non-endovascular treatment |
Advantages: Endovascular ED Treatment vs Conventional Surgical (Penile Implant)
|
Feature |
Penile Prosthesis Surgery |
Pudendal Angioplasty / Venous Embolisation |
|
Major Incision, Stitches |
Yes — penile or perineal surgical incision |
No — tiny needle entry at groin only |
|
Anaesthesia |
General or spinal anaesthesia always |
Local anaesthesia + IV sedation only |
|
Natural Erection Preserved? |
No — natural tissue permanently altered |
Yes — natural erection mechanism intact |
|
Reversible? |
No — permanent device, irreversible |
Yes — arteries and veins remain accessible |
|
Blood Loss |
Surgical blood loss + transfusion risk |
Minimal — no bone, no organ removed |
|
Hospital Stay |
2–5 days |
Same-day or overnight |
|
Recovery |
4–6 weeks |
Return to desk work in 3–5 days |
|
Can Be Repeated? |
Reoperation complex and risky |
Yes — repeat procedure safely feasible |
|
Best Suited For |
All types — AFTER all other treatments fail |
Arterial or venous ED — BEFORE surgical implant |
|
Treatment |
Brief Overview |
|
Lifestyle + Medical Optimisation |
First step for all vascular ED — smoking cessation, aerobic exercise, glycaemic control, dyslipidaemia treatment (statins), testosterone optimisation. Independent IIEF improvement documented for each intervention. |
|
PDE5 Inhibitors (Sildenafil, Tadalafil, Vardenafil) |
First-line pharmacological treatment — enhances cavernous smooth muscle relaxation. Effective for mild-moderate vascular ED. Limited efficacy in severe arterial insufficiency or complete venous leak. If two PDE5 inhibitors at adequate doses have failed: Doppler assessment before further treatment. |
|
Vacuum Erection Device |
Non-pharmacological option. Negative pressure draws blood into the corpus cavernosum; constriction ring traps it. No systemic side effects. Useful when PDE5 inhibitors are contraindicated (nitrate users) or in PDE5i non-responders. |
|
Intracavernosal Injection (ICI) Therapy |
Self-injection of alprostadil (PGE1) directly into the corpus cavernosum — produces erection independent of stimulation in 80–90% of patients. Works when oral medications have failed. Risk of priapism if dose is too high — medical emergency if erection lasts > 4 hours. |
|
Shockwave Therapy (LiSWT) |
Low-intensity acoustic waves delivered to the penile corpus cavernosum — promotes angiogenesis and endothelial repair. Best evidence for mild to moderate arteriogenic ED (PSV 25–35 cm/s). Typically 12 sessions over 6 weeks. No needles, no medication, no anaesthesia. |
|
PRP / P-Shot |
Platelet-rich plasma from patient's own blood injected into corpus cavernosum. Growth factors promote cavernous tissue repair and angiogenesis. Emerging evidence — modest IIEF improvement in mild-moderate ED. Often combined with shockwave therapy. Not a substitute for angioplasty in confirmed severe arterial stenosis. |
|
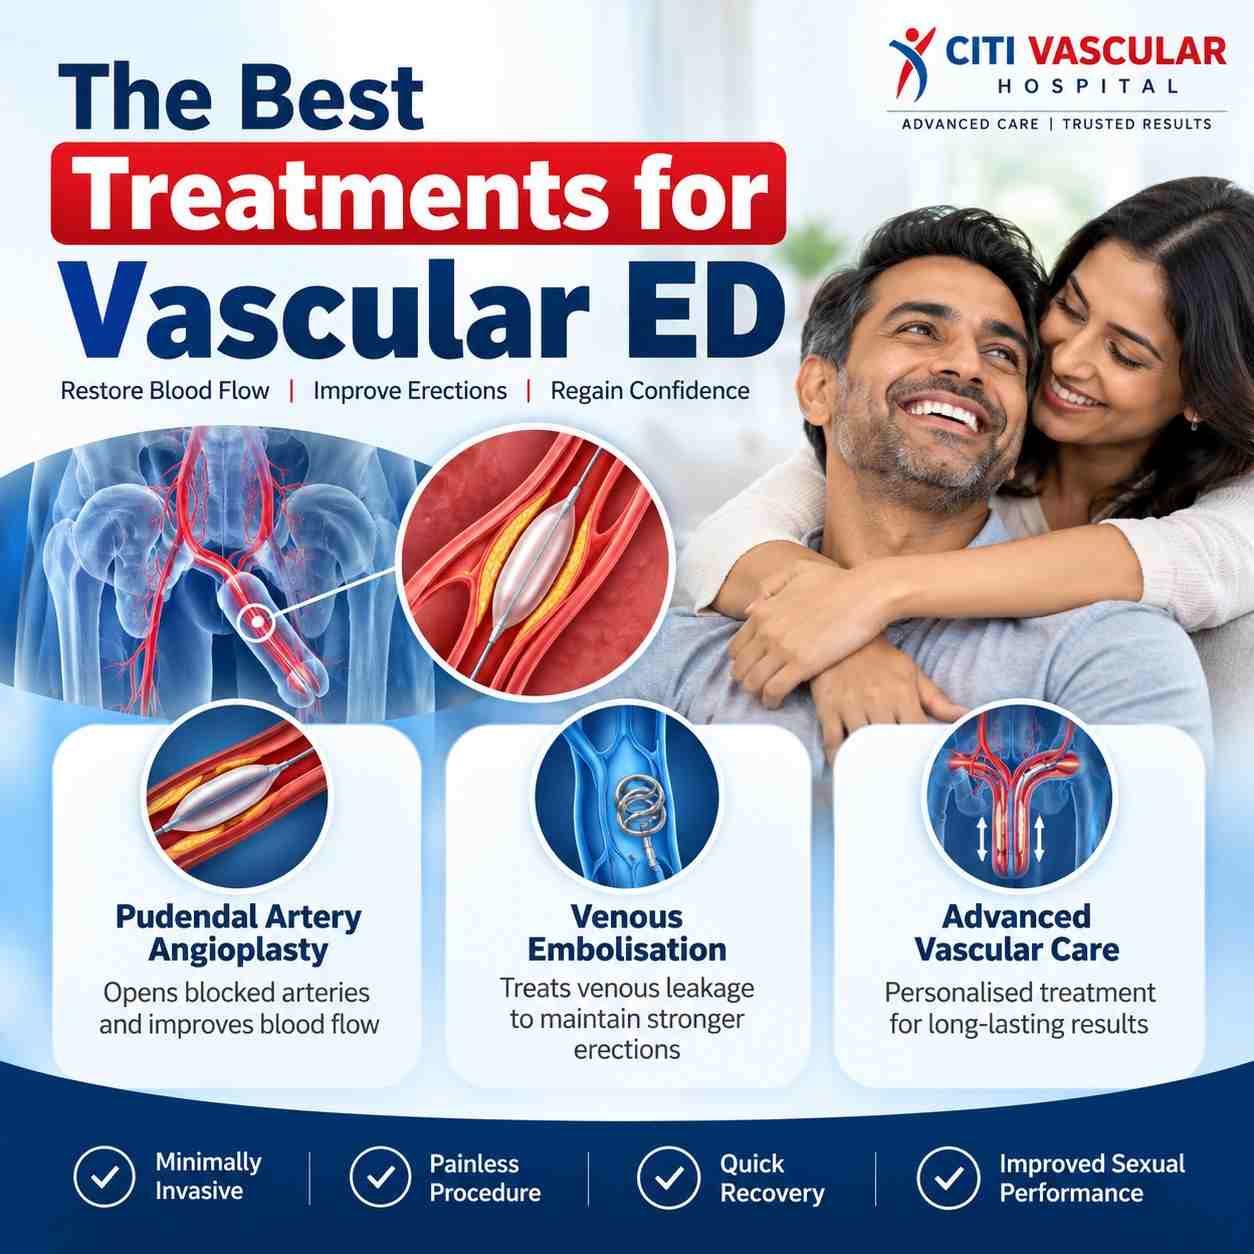
Catheter-based balloon angioplasty opens the stenosed internal pudendal artery under fluoroscopic guidance. Directly treats the arterial cause of ED. For: PSV < 25 cm/s | focal stenosis on CTA | age < 60 | failed PDE5i. 60–80% IIEF improvement (published series). Local anaesthesia + IV sedation. Same-day discharge. See dedicated page for full details. |
|
|
Embolisation of incompetent internal pudendal veins and cavernous veins reduces abnormal venous outflow in venous leak ED. For: EDV > 5 cm/s + RI < 0.75 | adequate PSV | failed PDE5i. 60–80% IIEF improvement (published series). Venous access via groin. Same-day discharge. See dedicated page for full details. |
|
|
Penile Prosthesis (Implant) |
Inflatable penile prosthesis implanted surgically — most reliable treatment (> 90% patient satisfaction). Appropriate as FINAL option when all above treatments have failed. Irreversible — natural erectile tissue permanently altered. General/spinal anaesthesia required. |
The cost of vascular ED treatment in Hyderabad at Citi Vascular Centre varies depending on the procedure required and the complexity of the individual case. Indicative ranges:
|
Treatment |
Approximate Cost Range |
|
Pharmacological Penile Doppler Assessment |
Rs 3,000 – Rs 8,000 — the essential diagnostic investigation before endovascular treatment |
|
CT Pelvic Angiography (for arterial ED planning) |
Rs 5,000 – Rs 12,000 — if not done externally |
|
Internal Pudendal Artery Angioplasty |
Rs 80,000 – Rs 1,50,000 — all-inclusive package (procedure, DSA, anaesthesia, ward stay, follow-up) |
|
Pelvic Venous Embolisation |
Rs 80,000 – Rs 1,50,000 — all-inclusive package |
|
Shockwave Therapy (full course) |
Rs 20,000 – Rs 60,000 — typically 10–12 sessions |
Exact cost estimate provided after pharmacological Doppler classification and CT/venography if indicated
Insurance coverage available for endovascular procedures when medically indicated — team assists with pre-auth at no extra charge
0% EMI facility available for eligible patients — ask care coordinator at booking
All consultations strictly confidential | Written itemised estimate before any commitment
WhatsApp 73375 83901 with Doppler report or clinical summary for advance cost estimate